For your patients
-
Earlier intervention, before symptoms drive a visit
-
Fewer HF hospitalizations and ED visits
-
Care that continues between appointments
-
A call from your clinic - not a stranger

CIED heart failure monitoring, managed end to end by CV Remote Solutions. No new staffing. No new software. No new workflow to build. Just a clear path from "we should be doing this," to a program that runs.
Implanted devices have been collecting heart failure diagnostics for years - thoracic impedance, night heart rate, activity, arrhythmia burden. In most clinics, that data arrives somewhere and stops. A heart failure monitoring program is simply the decision to read it and act.
BE HONEST ABOUT THE BARRIER
Nearly every clinic that hasn't started a heart failure monitoring program cites one of these three problems . . .
It sits between heart failure and the device clinic, so it belongs to everyone and no one. Now, the work belongs to us.
Your device clinic is already at capacity, and no one wants to be the one who adds to it. With CVRS, the review work never reaches your team.
Enrollment, education, scheduling, chasing disconnected monitors. Real work, no obvious home. It has one. It's ours.

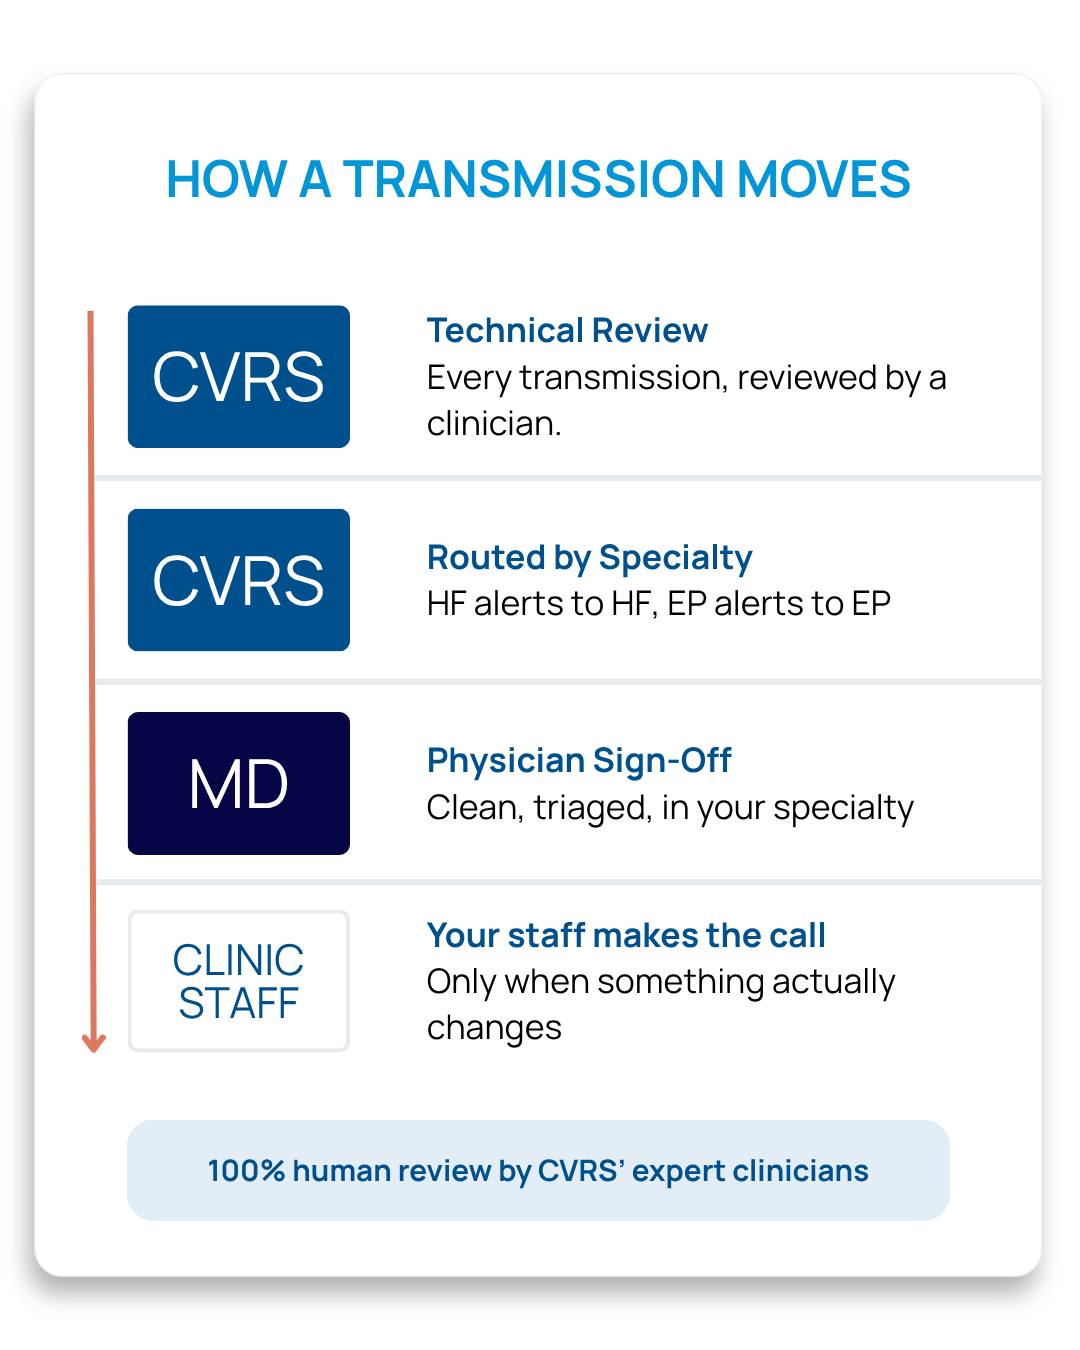
Both times its a clinical decision, not data handling. Everything in front of those two moments is ours.
Published time-and-motion data puts first-line review at 9.4-13.5 minutes of clinic staff time per remote transmission, plus 17.3 minutes per patient per year in calls, troubleshooting, triage, and scheduling. That's the part we take.
WHY US
One of the longest heart failure remote monitoring track records in the field
Presented at HFSA 2026 by CVRS co-founder Amber Seiler
Published work on alert reduction and remote monitoring workflows
Every transmission is reviewed by a CVRS clinical expert